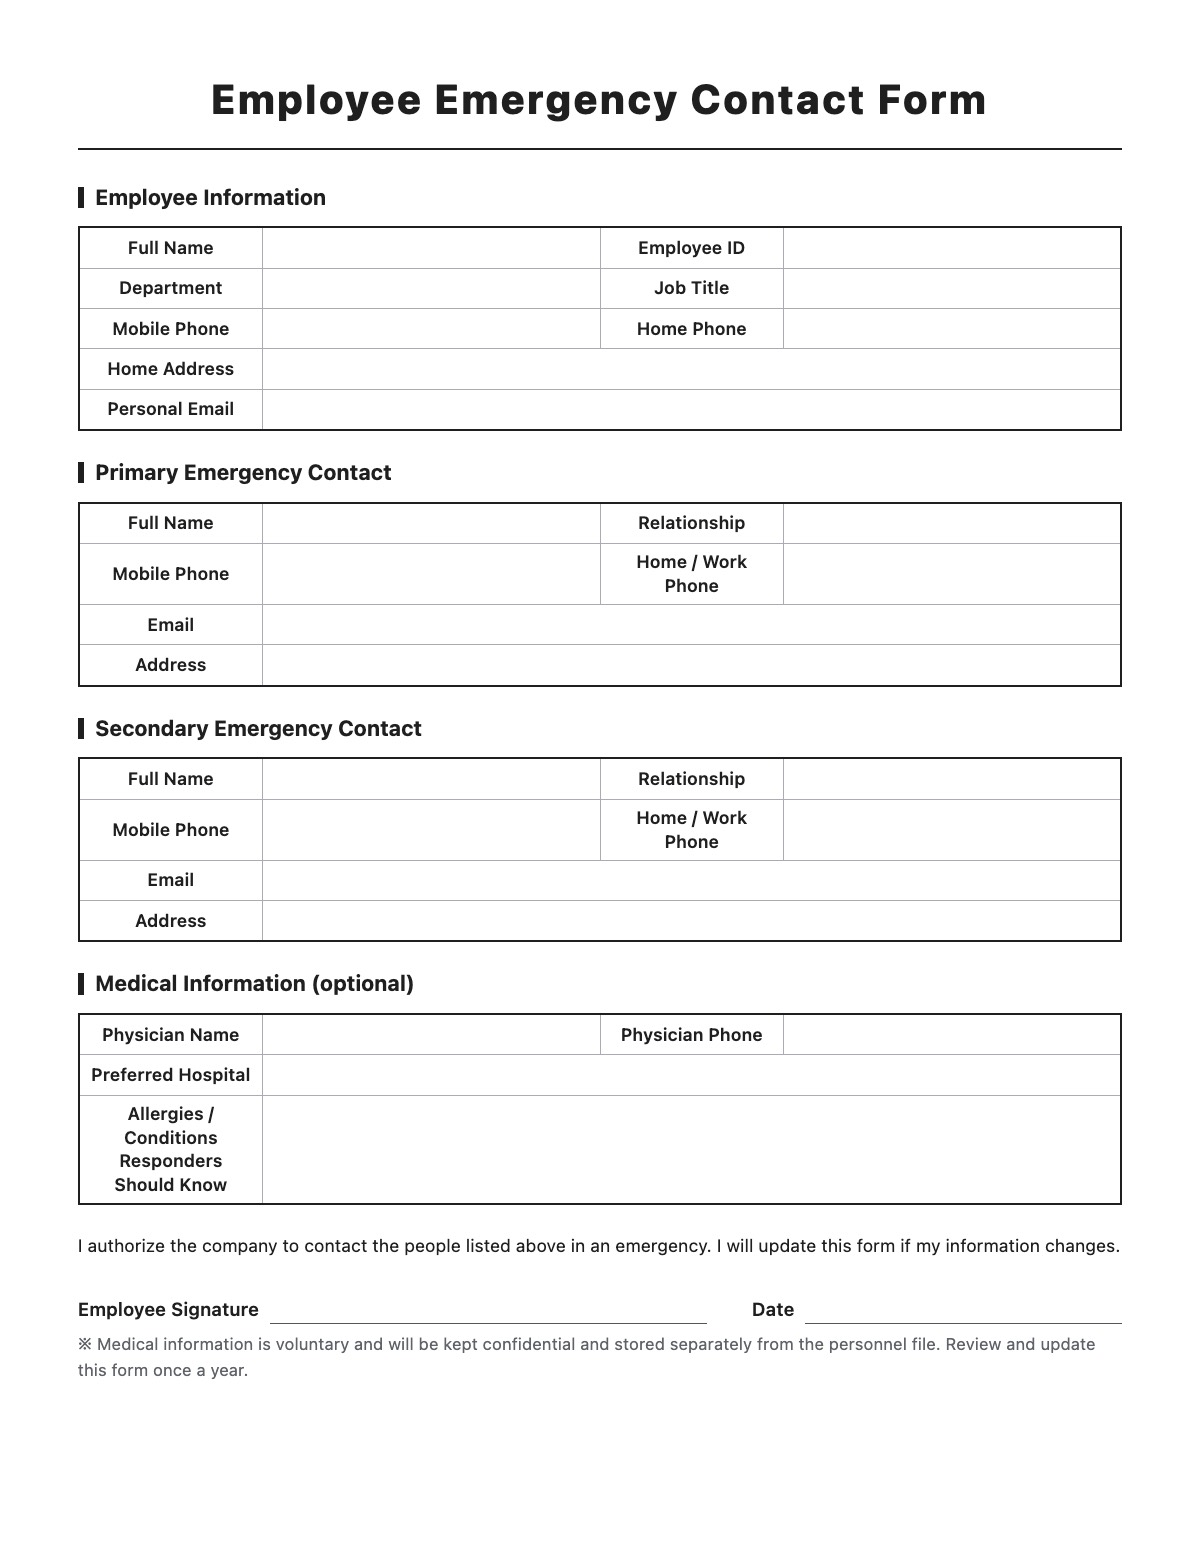
Employee Emergency Contact Form
Employee Information
| Full Name | Employee ID | ||
|---|---|---|---|
| Department | Job Title | ||
| Mobile Phone | Home Phone | ||
| Home Address | |||
| Personal Email | |||
Primary Emergency Contact
| Full Name | Relationship | ||
|---|---|---|---|
| Mobile Phone | Home / Work Phone | ||
| Address | |||
Secondary Emergency Contact
| Full Name | Relationship | ||
|---|---|---|---|
| Mobile Phone | Home / Work Phone | ||
| Address | |||
Medical Information (optional)
| Physician Name | Physician Phone | ||
|---|---|---|---|
| Preferred Hospital | |||
| Allergies / Conditions Responders Should Know | |||
I authorize the company to contact the people listed above in an emergency. I will update this form if my information changes.
Employee Signature
Date
※ Medical information is voluntary and will be kept confidential and stored separately from the personnel file. Review and update this form once a year.